
How to Step Away From Heel Pain for Good
Heel Pain Is More Common Than You Think — Here’s What’s Causing It
Heel pain affects nearly 2 million Americans every year — and if you’re dealing with it right now, you’re far from alone.
Before diving deeper, here are the most common causes:
- Plantar fasciitis — inflammation of the tissue band along the bottom of the foot; the #1 cause
- Achilles tendinitis — overuse injury affecting the tendon at the back of the heel
- Heel spurs — bony growths on the heel bone, often linked to plantar fasciitis
- Retrocalcaneal bursitis — swelling of the fluid-filled sac behind the heel
- Stress fractures — tiny bone cracks from repetitive impact
- Sever’s disease — growth plate irritation in active children aged 8–14
- Tarsal tunnel syndrome — nerve compression causing burning or tingling in the heel
- Bone bruise — deep bruising of the heel’s fatty pad from a hard impact
Whether your pain hits hardest with those first steps out of bed or builds up slowly after a long day on your feet, it’s your body signaling that something needs attention.
The frustrating part? Many people push through it — and that’s exactly when a manageable condition becomes a chronic problem. People in the US visit a physician more than 1 million times a year just for heel pain, making it one of the most common musculoskeletal complaints treated by orthopaedic specialists.
The good news: up to 90% of cases resolve without surgery when treated early and correctly.
This guide breaks down what’s actually causing your heel pain, how it’s diagnosed, and what works to get you back on your feet.
Understanding Heel Pain: Common Causes and Anatomy
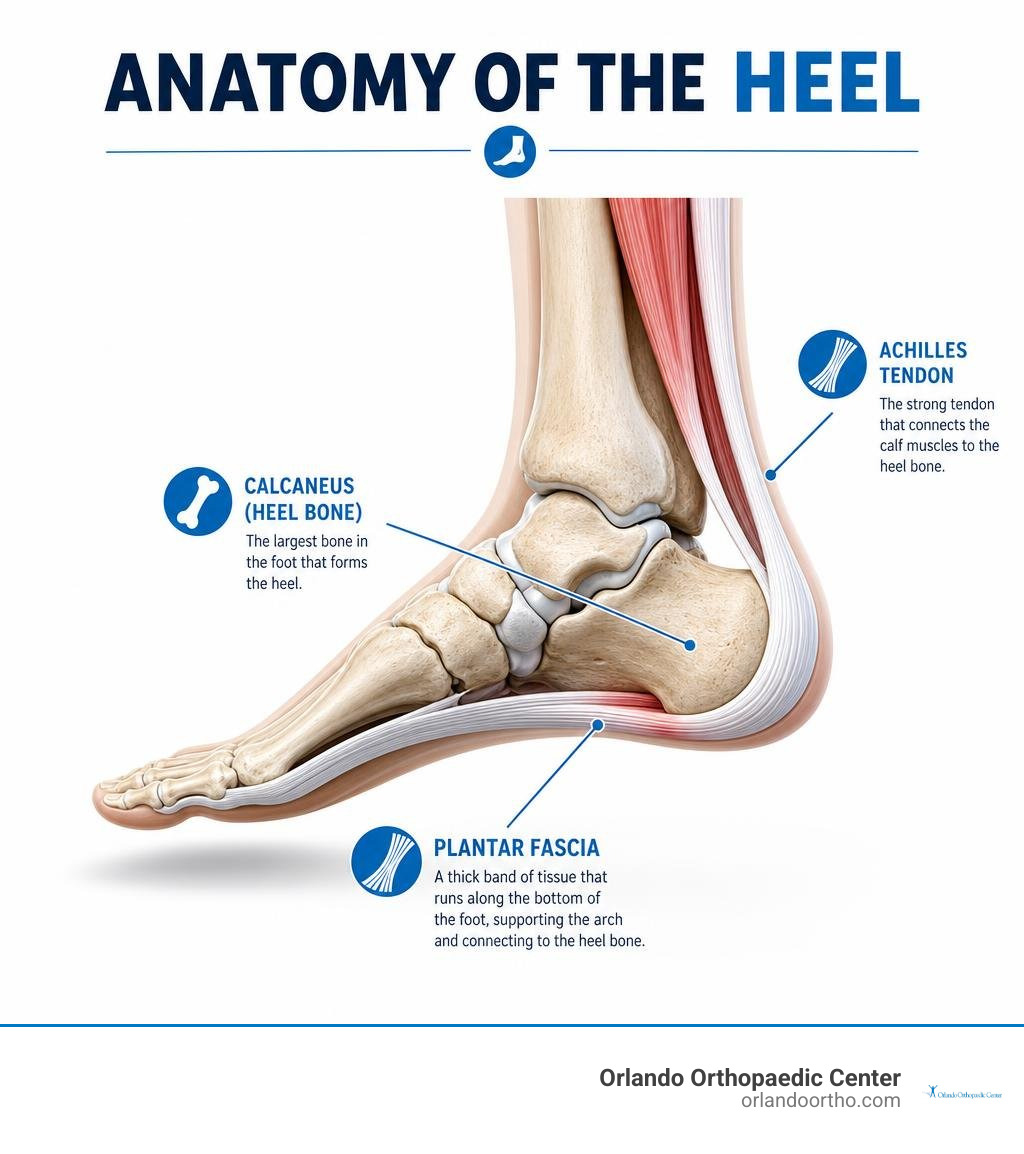
To get to the bottom of your discomfort, it helps to take a quick peek beneath the skin. Your foot is a masterwork of biological engineering designed to absorb immense forces every single day. At the foundation of it all lies the calcaneus (your heel bone), which happens to be the largest bone in your foot.
Connecting to and wrapping around the calcaneus are two vital mechanical structures:
- The Achilles Tendon: The body’s longest and strongest tendon, attaching your calf muscles directly to the back of the calcaneus bone.
- The Plantar Fascia: A thick, fibrous band of connective tissue running along the sole of your foot, stretching from your calcaneus all the way to the base of your toes.
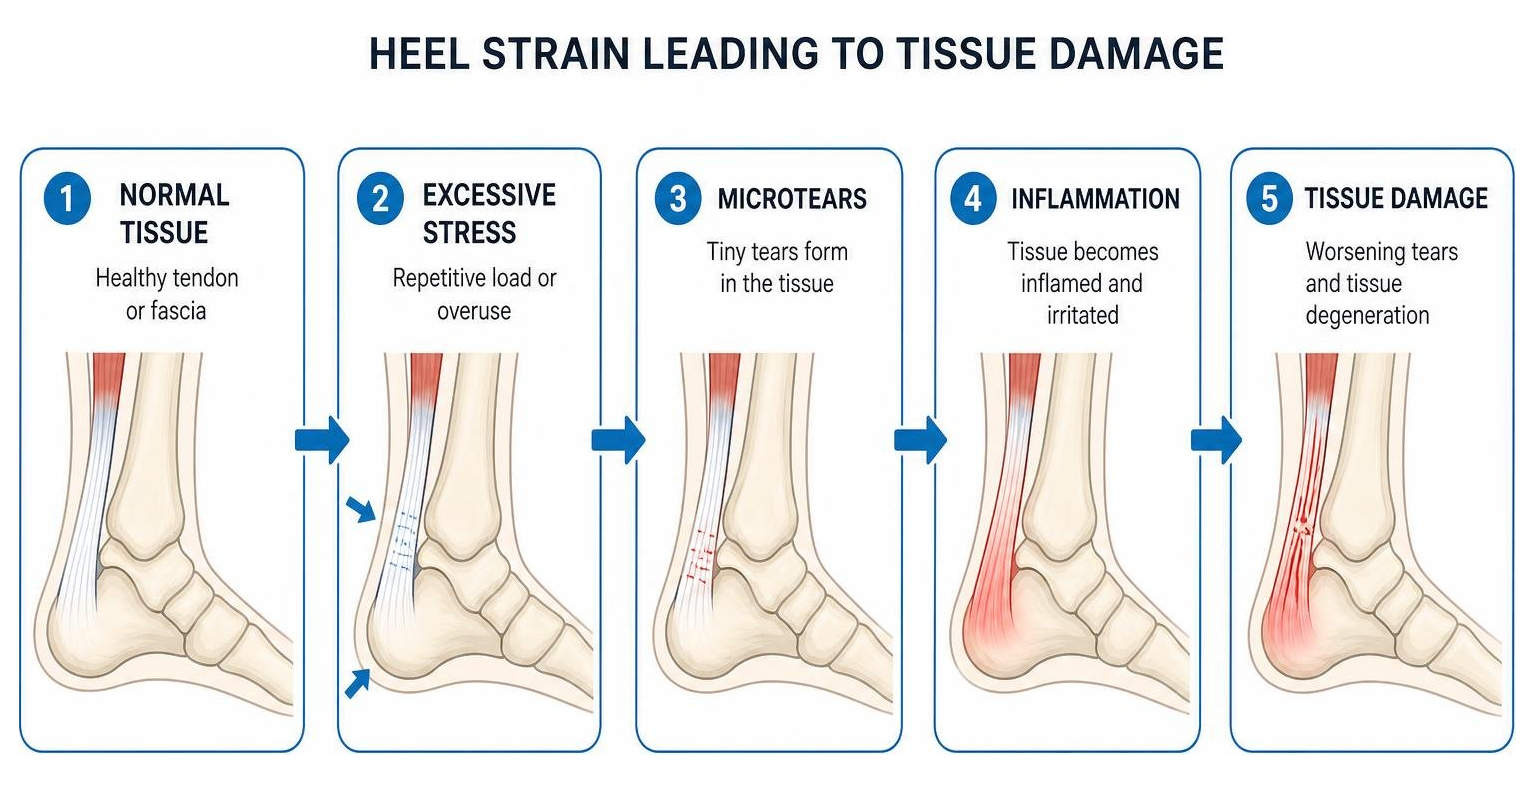
Think of your plantar fascia as a flexible bowstring supporting the arch of your foot. Whenever you stand, run, or leap, this structure acts as a central shock absorber. However, when these structures are subjected to excessive stress or repetitive strain, inflammation and tiny structural tears can occur. Unraveling these complex mechanics is key to understanding root foot causes behind every sharp ache or dull throbbing sensation you feel.
Is Plantar Fasciitis Causing Your Heel Pain?
If you experience a sharp, stabbing sensation on the bottom of your foot right when your feet hit the floor in the morning, plantar fasciitis is almost certainly the culprit. It stands as the single most common cause of heel pain, affecting roughly 10% of the population over the course of a lifetime.
To understand why it hurts so much after resting, we have to look at the windlass mechanism. When you sleep or sit for prolonged periods, your plantar fascia relaxes and shortens. Upon taking those initial morning steps, your weight suddenly flattens your foot arch, placing immediate mechanical tension across a tight, inflamed band of tissue. This produces microscopic tears and intense localized inflammation near the calcaneal tuberosity.
Interestingly, medical researchers note that chronic, long-term cases are often better described as plantar fasciosis. Rather than acute active inflammation, histology shows collagen degeneration and micro-thickening of the tissue (often exceeding 4 mm when measured on clinical imaging).
If you’d like to dive deeper into this condition, check out the Mayo Clinic guide on plantar fasciitis or review our comprehensive plantar fasciitis overview to see how custom care plans can relieve chronic arch tension.
Other Mechanical and Traumatic Sources of Heel Pain
While plantar fasciitis takes top billing, it is far from the only suspect when it comes to mechanical or traumatic heel injuries:
- Achilles Tendinitis & Tendinosis: Inflammation or chronic tissue breakdown of the Achilles tendon often causes pain behind the heel rather than underneath it. It is particularly common among runners and jumping athletes who rapidly increase their training intensity.
- Calcaneal Spurs (Heel Spurs): Bony projections that develop on the underside of the heel bone. Interestingly, heel spurs are present in 45% to 85% of people with plantar fasciitis, but over 15% of the general population has asymptomatic spurs! They are usually a symptom of chronic fascia tension rather than the direct source of pain. You can learn about foot bone spurs and how they are addressed conservatively.
- Calcaneal Stress Fractures: Tiny cracks in the heel bone resulting from repetitive high-impact activities. In military recruits, calcaneal stress fractures account for up to 20% of all lower extremity stress fractures.
- Bone Bruises: Stepping hard on a sharp rock or landing awkwardly can bruise the fatty cushion beneath your calcaneus, causing deep, pinpoint tenderness when walking.
- Retrocalcaneal Bursitis: Inflammation of the small, fluid-filled sac (bursa) situated between your heel bone and the Achilles tendon. Wearing stiff, back-clipping footwear like high-heeled pumps can irritate this area.
- Heel Pad Atrophy: As we age, the protective fat cushion under our calcaneus naturally thins out. Unlike plantar fasciitis, heel pad pain feels like a broad, dull ache right under the middle of the heel that worsens with prolonged standing on hard surfaces.
For a deeper dive into these complex biomechanical conditions, you can consult this comprehensive NCBI clinical review on plantar heel conditions.
Growth Plate Irritation, Nerve Entrapment, and Systemic Causes
Not all heel discomfort comes from simple wear and tear on tendons or fascia:
- Sever’s Disease (Calcaneal Apophysitis): If your child aged 8 to 14 complains of severe heel soreness after soccer or basketball practice, it is rarely plantar fasciitis. Instead, it is likely Sever’s disease—an overuse irritation of the growing calcaneal growth plate caused by the repetitive pull of the Achilles tendon during rapid growth spurts.
- Nerve Entrapment Disorders: Conditions like tarsal tunnel syndrome or entrapment of the Baxter nerve occur when peripheral nerves traveling along the inner ankle become compressed. This produces burning, tingling, or electric shock-like sensations that radiate across the sole and heel pad.
- Systemic Inflammatory Illnesses: Did you know that roughly 16% of patients presenting with heel pain have an underlying systemic disease? Conditions like rheumatoid arthritis, psoriatic arthritis, ankylosing spondylitis, and gout can all trigger severe enthesitis (inflammation where tendons attach to bone).
You can explore a full breakdown of systemic and localized symptoms in the Cleveland Clinic heel overview.
Identifying Risk Factors for Heel Conditions
Why do some people develop severe foot discomfort while others log thousands of miles completely pain-free? A variety of intrinsic and extrinsic risk factors play a role:
- Age: Plantar fasciitis and Achilles tendinopathies occur most frequently in adults between the ages of 40 and 50.
- Body Weight: Excess weight increases the mechanical shock load delivered to the calcaneus and plantar fascia with every step.
- Foot Mechanics: Having structurally flat feet (pes planus) or high arches (pes cavus) alters your weight distribution, straining the arch and Achilles insertion.
- Occupational Stress: Teachers, factory workers, healthcare professionals, and retail workers who spend long shifts standing on unforgiving concrete or tile floors face elevated risks.
- Exercise Dynamics: High-impact sports involving running, dancing, or rapid jumping—especially when performed on hard surfaces—can overtax foot tissue.
- Improper Footwear: Thin-soled, unsupportive shoes, worn-out sneakers, or rigid high heels lack essential arch support and shock absorption.
To help you understand how these factors overlap, we’ve organized them into a quick comparison reference below:
| Condition | Common Age Range | Key Mechanical Risk Factors | Typical Pain Location |
|---|---|---|---|
| Plantar Fasciitis | 40 – 60 years | Flat feet, high arches, sudden weight gain | Bottom of the heel; severe in the morning |
| Achilles Tendinitis | 30 – 50 years | Tight calf muscles, sudden increase in training | Back of the heel and along the tendon |
| Sever’s Disease | 8 – 14 years | Rapid growth spurts, high-impact youth sports | Back and sides of the calcaneus in kids |
| Heel Pad Atrophy | 60+ years | Natural tissue aging, prolonged hard-surface standing | Center of the heel cushion; diffuse aching |
| Stress Fracture | Any age (athletes/military) | Overtraining, osteoporosis, hard-surface running | Deep in the heel bone; constant weight-bearing pain |
Diagnostic Approaches for Persistent Foot Discomfort
When you visit an orthopaedic specialist for lingering foot pain, we start with a thorough clinical history and hands-on physical exam. We will inspect your foot both at rest and while bearing weight, checking your arch structure and ankle flexibility.

During the physical evaluation, we utilize targeted diagnostic tests:
- Palpation Testing: Pressing directly on the inner calcaneal tuberosity to reproduce plantar fascia pain, or feeling the back of the heel for localized Achilles tenderness.
- Passive Toe Dorsiflexion: Pulling your toes back toward your shin puts the plantar fascia on tension. If this increases your bottom-of-foot pain, it strongly points toward plantar fasciitis.
- Dorsiflexion-Eversion Test: Flexing and turning the foot outward while tapping behind the ankle bone helps us assess for nerve irritation in tarsal tunnel syndrome.
To rule out bone fractures, tumors, or structural abnormalities, we often order standing X-rays. If soft tissue damage, severe tendinosis, or hidden stress fractures are suspected, advanced imaging like musculoskeletal ultrasound or an MRI gives us a clear view of your soft tissues.
If you are suffering from persistent discomfort, you can consult this helpful MedlinePlus medical reference on foot evaluation or discover our specialized subspecialty foot and ankle medical care options tailored to your specific condition.
Effective Non-Surgical Treatments and Preventive Strategies
Here is the most reassuring statistic in all of orthopaedic medicine: up to 90% of patients with plantar heel pain recover fully using non-surgical conservative care within 6 to 12 months.
Our goal is always to calm tissue inflammation, correct biomechanical imbalances, and rebuild tissue strength.

First-Line Conservative Interventions
- Rest and Activity Modification: Switch high-impact running or aerobics to low-impact cardiovascular workouts like swimming or stationary cycling to give inflamed tissues time to heal.
- Targeted Ice Therapy: Rolling the arch of your foot over a frozen water bottle for 10 to 15 minutes twice a day cools inflamed fascia while providing a gentle self-massage.
- Daily Stretching Protocols: Flexible calves mean happy heels! Perform gentle daily stretches focusing on both the gastrocnemius and soleus calf muscles, as well as manual stretches pulling your toes gently backward.
- Custom Orthotics and Supportive Footwear: Avoid walking barefoot on hard floors, even inside your house! Wear well-cushioned shoes with built-in arch support. Custom orthotic inserts or silicone heel pads can cushion the calcaneus and relieve arch strain.
- Night Splints: Wearing a lightweight night splint keeps your ankle held at a neutral 90-degree angle while you sleep. This prevents the plantar fascia from contracting overnight, easing those terrible first steps in the morning.
- Medications and Taping: Short courses of over-the-counter NSAIDs (like ibuprofen or naproxen) can help manage acute flare-ups. Short-term supportive low-dye taping applied by a physical therapist provides instant structural relief.
Advanced Non-Surgical Options
If first-line remedies don’t fully resolve the issue after several weeks, advanced non-surgical modalities may be recommended:
- Physical Therapy: Specialized manual therapy, gait retraining, and targeted strengthening of the intrinsic foot muscles.
- Corticosteroid Injections: While a targeted steroid injection into the plantar fascia can provide profound short-term relief, repeated injections carry risks, including rupture of the fascia or fat pad atrophy. Consequently, they are used judiciously. (Note: Corticosteroid injections are rarely recommended for Achilles tendon conditions due to the risk of tendon rupture.)
Explore our full range of evidence-based non-surgical plantar fasciitis options to discover how targeted therapies can accelerate your recovery.
When to Seek Medical Evaluation and Potential Complications
While minor foot soreness often improves with home care, pushing through severe, unmanaged pain is a recipe for trouble.
Red Flag Symptoms Requiring Immediate Evaluation
You should schedule an evaluation with a specialist promptly if you notice:
- Inability to bear weight on your foot or walk safely.
- Numbness, tingling, or burning sensations radiating into your foot or toes.
- Visible deformity, popping sounds during an injury, or severe sudden swelling.
- Redness, warmth, or fever (which can indicate an underlying infection like osteomyelitis).
- Persistent pain that shows zero improvement after 2 to 3 weeks of home rest and icing.
- Note for Patients with Diabetes: If you have diabetes, any foot pain, swelling, or skin changes require immediate professional care to prevent serious complications.
The Hidden Complications of Untreated Heel Pain
Ignoring heel pain doesn’t just hurt your foot—it impacts your overall health. When you hobble or limp to protect a sore heel, you unconsciously alter your walking mechanics. Over time, this abnormal gait creates abnormal stress further up the kinetic chain, triggering secondary chronic pain in your knees, hips, and lower back.

Furthermore, chronic mobility loss often forces people into an unintended sedentary lifestyle. Decreased daily movement can lead to unwanted weight gain, cardiovascular decline, and emotional frustration or depression as you are forced to miss out on active hobbies and family fun.
For additional safety guidelines, review the official NHS medical guidance on foot symptoms.
Frequently Asked Questions
How long does conservative care take to resolve bottom-of-foot stiffness?
Most patients experience noticeable relief within 6 weeks of starting structured conservative treatments like daily calf stretches, ice therapy, and supportive orthotics. However, because tendon and fascial tissue heals slowly, full recovery typically takes anywhere from 3 to 12 months. Early intervention is key to speeding up this timeline!
Do calcaneal bone spurs directly cause bottom-of-foot discomfort?
No, heel spurs themselves are usually not the direct source of pain! Calcaneal spurs co-occur in 45% to 85% of people with plantar fasciitis, but over 15% of completely pain-free individuals have bone spurs too. Bone spurs are simply a sign that the plantar fascia has been pulling on the calcaneus over a long period. Pain relief comes from treating the inflamed soft tissue, not cutting away the bone spur.
Can changing your walking gait trigger secondary joint issues?
Yes, absolutely! When you limp or alter your foot strike to avoid heel pain, you shift uneven stress into your ankles, knees, hips, and lower back. This compensatory walking pattern frequently leads to secondary strain throughout your entire kinetic chain, which is why early medical diagnosis is so crucial.
Conclusion
Living with heel pain can feel exhausting, but you do not have to accept persistent foot pain as an inevitable part of aging or an active lifestyle. With an accurate diagnosis, targeted stretching routines, proper footwear, and simple conservative care, standard non-surgical treatments help up to 90% of people step away from heel pain for good.
At Orlando Orthopaedic Center, our team of foot and ankle subspecialists is dedicated to helping you regain your mobility and live pain-free. If persistent foot pain is keeping you on the sidelines, don’t wait for a quick fix to turn into a chronic condition. Schedule an appointment for specialized foot care with our team today and take your first comfortable step toward lasting relief!


